

Thyroid cancer · Papillary · Follicular · Long-term follow-up
Thyroid cancer, followed closely and lived with well.
Most thyroid cancers are slow-growing and highly curable. Good outcomes depend on the right surgery, treatment matched to risk, and years of thoughtful follow-up with an endocrinologist.

Types of thyroid cancer
Papillary
About 85% of cases. Often found in a nodule by ultrasound, grows slowly, excellent long-term survival.
Follicular and oncocytic
Less common, more likely to spread through the bloodstream than to lymph nodes, still very treatable.
Medullary
Arises from calcitonin-producing cells; a quarter are inherited, so genetic testing is offered.
Anaplastic
Rare and aggressive; managed urgently with a specialized oncology team.
How it is treated
Care is staged to the cancer and to you. Small, low-risk papillary cancers are increasingly treated with less: a partial thyroidectomy, or in selected cases active surveillance with ultrasound instead of immediate surgery.
Follow-up: what it involves
- Thyroglobulin, a protein made only by thyroid tissue, acts as a blood marker after total thyroidectomy. Undetectable levels are reassuring; a rising level prompts imaging.
- Levothyroxine replaces thyroid hormone and, for higher-risk cancers, is dosed to keep TSH low for a period of time. For low-risk disease a normal TSH is the goal, which avoids the bone and heart effects of over-replacement.
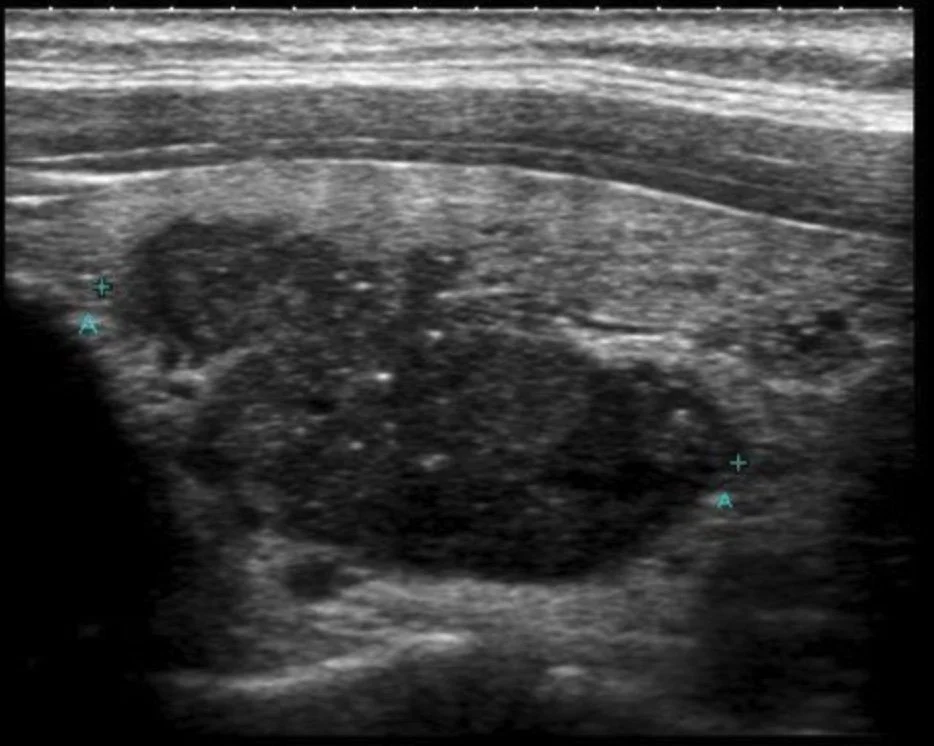
- Neck ultrasound at 6 to 12 months, then at intervals set by your response to treatment.
- Dynamic risk reassessment: your risk category is updated at each visit based on results, and most people move into the lowest-risk group and need less monitoring over time.
- Calcium and parathyroid function are checked after total thyroidectomy, since the parathyroid glands sit beside the thyroid.
Dr. Hasan is experienced in the long-term management of differentiated thyroid cancer, including thyroid hormone dosing, thyroglobulin and ultrasound surveillance, and coordination with thyroid surgeons and nuclear medicine.
Common questions
Is thyroid cancer curable?
For papillary and follicular cancers, long-term survival exceeds 95%, and most people live a normal lifespan. Follow-up is lifelong because recurrences, when they happen, are treatable.
Do I need radioactive iodine?
Not always. Low-risk cancers usually do not benefit. Intermediate and higher-risk cancers often do, and the decision is based on your pathology report.
Will I feel normal on levothyroxine?
Most people do once the dose is right. If TSH is intentionally kept low for cancer control, the dose is relaxed over time as risk falls.
Can follow-up be done by telehealth?
Largely, yes. Blood tests and ultrasound are done locally and reviewed by video, with in-person visits when an examination is needed.
Related conditions
In Wexford or by telehealth in PA and OH